Choosing orthopedic surgical instruments is not a simple purchasing exercise. It is a clinical decision that can influence handling, accuracy, efficiency, and patient safety.
Orthopedic surgeon Dr. James Andrews is widely associated with the warning, “There is no such thing as minor surgery.” His point applies directly to instrument selection. A small weakness in a rongeur, drill guide, or retractor may become significant during a demanding procedure. The correct choice begins with the operation, not the catalog photograph. Surgeons should examine instrument geometry, grip comfort, jaw alignment, balance, and visibility within the surgical field. The instrument should feel controlled, even when gloves are wet or fatigue develops.
A reliable evaluation also considers material quality, sterilization compatibility, maintenance, and traceability. Stainless steel may resist corrosion, but performance still depends on manufacturing precision and care. Powered systems require attention to torque, battery life, vibration, and cleaning instructions. Trial handling can reveal problems that specifications hide. That detail matters.
Hospitals should involve orthopedic surgeons, nurses, sterile-processing staff, and procurement specialists. Each group sees a different risk. A clamp that feels excellent to one surgeon may slow another user. No checklist is perfect. That is worth admitting. However, documented testing, supplier credentials, training support, and evidence of consistent quality create a stronger basis for comparison. This guide explains how to assess orthopedic surgical instruments with practical judgment, technical awareness, and respect for the realities of the operating room.
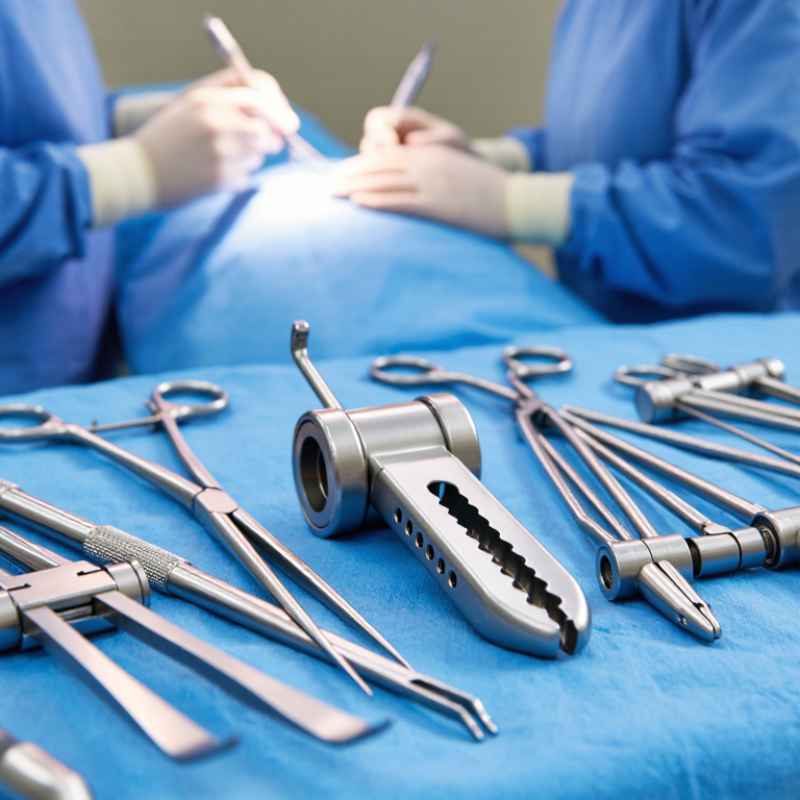
How to Choose Orthopedic Surgical Instruments?
Map the operation before opening the tray. Start with anatomy: bone shape, joint surface, nearby vessels, nerves, and soft tissue thickness. A narrow corridor may require slim, angled instruments, while broad exposure allows stronger, straighter tools. The planned approach also changes the working direction. For example, a lateral approach can demand offset handles to protect the surgeon’s wrist and preserve visibility. Small details matter.
Match each instrument to a defined function. Cutting tools should create controlled planes, not rough damage. Graspers need a secure hold without crushing fragile tissue. Retractors should provide steady exposure with limited pressure. Drills, reamers, and guides must support accurate alignment and depth control. Check measurement markings against the surgical plan, and confirm compatibility with the intended implants or fixation method. A tool can look familiar yet perform poorly in different anatomy.
Experienced teams also inspect balance, grip, locking action, and cleaning quality before use. I have seen instrument choice change during surgery when swelling narrowed the field or bone density differed from imaging. That flexibility is useful, but it should not replace preparation. One weakness is assuming every step follows the plan. It does not. Review the sequence with the team, identify backup instruments, and question whether each tool improves access, precision, or tissue protection. If its purpose is unclear, leave it out.
Instrument selection should begin with jaw geometry, not appearance. A bone rongeur needs jaws that match the intended cutting angle and tissue access. Serration depth affects grip on dense cortical bone. A narrow jaw may improve visibility, but it can concentrate force and deform sooner. Small details matter.
Working length must fit the surgical approach, patient anatomy, and imaging plan. Excess length can reduce tactile feedback. Insufficient length may force awkward wrist positions. In instrument evaluations, check jaw closure under load, not only on a tray. Measure it twice. ISO 7153-1 and ASTM F899 provide useful material and design references for surgical instruments, but neither replaces procedure-specific testing.
Tolerance data should be documented in measurable terms. Record jaw-tip alignment, handle play, cutting-edge offset, and closure force. A 0.2 mm mismatch may seem minor, yet it can leave uneven bites or require repeated manipulation. WHO’s Safe Surgery Saves Lives program estimated 234 million major operations worldwide each year, with complications occurring in roughly 3–16% of hospital surgeries. That broad range shows why reliable instrument performance deserves attention. Reports from the U.S. FDA also repeatedly identify surgical-tool problems involving breakage, malfunction, and incomplete inspection. The uncomfortable part is that a familiar instrument can still fail quietly. Do not confuse comfort with precision.
When choosing orthopedic surgical instruments, material selection deserves close attention.
ASTM F899 provides a recognized framework for stainless steel used in surgical instruments. However, an ASTM reference alone does not guarantee reliable performance. Ask for the exact steel grade, heat-treatment records, inspection data, and material traceability.
316L stainless steel is often selected for its corrosion resistance and low carbon content. The lower carbon level helps reduce carbide precipitation after welding or high-temperature processing.
Its typical 2–3% molybdenum content improves resistance to pitting, especially when instruments contact saline, blood, or aggressive cleaning solutions.
Small details matter. A rough surface can still trap residue and develop stains, even when the alloy is appropriate.
Inspect the instrument under bright light. Check joints, serrated jaws, cutting edges, and narrow channels. They should move smoothly without catching. Confirm that repeated cleaning and sterilization cycles will not weaken the finish or affect alignment.
I would not approve a purchase from a material certificate alone. The design, hardness, polishing quality, and manufacturing controls also influence safety and service life.
This is where evaluation can become less certain.
A polished sample may look excellent, while production batches vary. Request representative samples and test them under actual workflow conditions.
That practical step often reveals problems that specifications miss.
How to Choose Orthopedic Surgical Instruments?
Reprocessing validation should influence orthopedic instrument selection, not appear as an afterthought. Choose instruments with clear cleaning, inspection, packaging, and sterilization instructions. ANSI/AAMI ST79 identifies common steam exposure parameters: 121°C for 30 minutes in gravity cycles, or 132°C for four minutes in dynamic-air-removal cycles. These figures are not universal shortcuts. The device manufacturer’s validated instructions, load configuration, and sterilizer performance remain essential. Small details matter. A narrow cannula can retain moisture, bone debris, or trapped air after washing. Hinges and serrations need direct visual inspection under adequate lighting. Complex designs deserve documented testing.
The World Health Organization reported that healthcare-associated infections affect approximately 7% of patients in high-income countries and 15% in low- and middle-income countries. Reliable reprocessing helps reduce preventable exposure, although it cannot replace staff training or routine monitoring. The Centers for Disease Control and Prevention recommends steam sterilization for heat-resistant critical devices, including instruments entering sterile tissue. Select instruments that tolerate repeated 121–132°C cycles without corrosion, distortion, or loss of function. Record biological indicators, chemical indicators, exposure time, temperature, and drying results. Do not rely on a green indicator alone. It confirms limited conditions, not perfect sterility. In practice, teams may validate one tray successfully, then overlook a different arrangement. That is a weakness worth challenging. Recheck dense orthopedic sets, especially after repairs or design changes. Our assumptions can fail quietly.
Minimum exposure times vary by sterilizer cycle and air-removal method. The values below represent commonly specified exposure conditions for wrapped healthcare products and must be confirmed against the instrument and sterilizer manufacturer’s validated instructions for use.
Document compliance should guide orthopedic instrument selection, not follow it as an afterthought. I look for suppliers that maintain ISO 13485-based quality systems and controlled technical records. Each instrument should have clear specifications, inspection criteria, and maintenance instructions. These details support consistent purchasing and safer clinical workflows.
UDI information helps identify an instrument through its production and distribution history. Check whether the UDI is readable, durable, and linked to the correct device records. The package label should match the instrument, catalog description, and supplied documentation. A mismatch can create delays during receiving or inventory checks. Small errors matter.
Lot-level traceability is equally important. Records should connect each instrument or set to its lot, production date, inspection results, and shipment details. Ask how quickly the supplier can provide these records during an investigation. In practice, some teams rely too heavily on spreadsheets. That approach can fail when entries are incomplete or copied incorrectly. A controlled electronic system is stronger, but only when staff use it consistently. Review training logs, change-control procedures, and sample traceability reports before approval. A polished document is not enough. Reliable selection depends on evidence that remains accurate from purchase to surgical use.
WhatsApp us